
NEET MDS Lessons
Orthodontics
BONES OF THE SKULL
A) Bones of the cranial base:
A) Fontal (1)
B) Ethmoid (1)
C) Sphenoid (1)
D) Occipital (1)
B) Bones of the cranial vault:
1. Parietal (2)
2. Temporal (2)
C) Bones of the face:
Maxilla (2)
Mandible (1)
Nasal bone (2)
Lacrimal bone (2)
Zygomatic bone (2)
Palatine bone(2)
Infra nasal concha (2)
FUSION BETWEEN BONES
1. Syndesmosis: Membranous or ligamentus eg. Sutural point.
2. Synostosis: Bony union eg. symphysis menti.
3. Synchondrosis: Cartilaginous eg. sphenoccipital, spheno-ethmoidal.
GROWTH OF THE SKULL:
A) Cranium: 1. Base 2. Vault
B) Face: 1. Upper face 2.Lower face
CRANIAL BASE:
Cranial base grows at different cartilaginous suture. The cranial base may be divided into 3 areas.
1. The posterior part which extends from the occiput to the salatercica. The most important growth site spheno-occipital synchondrosis is situated here. It is active throughout the growing period and does not close until early adult life.
2. The middle portion extends from sella to foramen cecum and the sutural growth spheno-ethmoidal synchondrosis is situated here. The exact time of closing is not known but probably at the age of 7 years.
3. The anterior part is from foramen cecum and grows by surface deposition of bone in the frontal region and simultaneous development of frontal sinus.
CRANIAL VAULT:
The cranial vault grows as the brain grows. It is accelerated at infant. The growth is complete by 90% by the end of 5th year. At birth the sutures are wide sufficiently and become approximated during the 1st 2 years of life.
The development and extension of frontal sinus takes place particularly at the age of puberty and there is deposition of bone on the surfaces of cranial bone.
Mixed Dentition Analysis: Tanaka & Johnson Analysis
This analysis is crucial for predicting the size of unerupted permanent teeth based on the measurements of erupted teeth, which is particularly useful in orthodontics.
Mixed Dentition Analysis
Mixed dentition refers to the period when both primary and permanent teeth are present in the mouth. Accurate predictions of the size of unerupted teeth during this phase are essential for effective orthodontic treatment planning.
Proportional Equation Prediction Method
When most canines and premolars have erupted, and one or two succedaneous teeth are still unerupted, the proportional equation prediction method can be employed. This method allows for estimating the mesiodistal width of unerupted permanent teeth.
Procedure for Proportional Equation Prediction Method
-
Measurement of Teeth:
- Measure the width of the unerupted tooth and an erupted tooth on the same periapical radiograph.
- Measure the width of the erupted tooth on a plaster cast.
-
Establishing Proportions:
- These three measurements form a proportion that can be solved to estimate the width of the unerupted tooth on the cast.
Formula Used
The following formula is utilized to calculate the width of the unerupted tooth:
[ Y_1 = \frac{X_1 \times Y_2}{X_2} ]
Where:
- Y1 = Width of the unerupted tooth whose measurement is to be determined.
- Y2 = Width of the unerupted tooth as seen on the radiograph.
- X1 = Width of the erupted tooth, measured on the plaster cast.
- X2 = Width of the erupted tooth, measured on the radiograph.
Application of the Analysis
This method is particularly useful in orthodontic assessments, allowing practitioners to predict the size of unerupted teeth accurately. By using the measurements of erupted teeth, orthodontists can make informed decisions regarding space management and treatment planning.
Growth is the increase in size It may also be defined as the normal change in the amount of living substance. eg. Growth is the quantitative aspect and measures in units of increase per unit of time.
Development
It is the progress towards maturity (Todd). Development may be defined as natural sequential series of events between fertilization of ovum and adult stage.
Maturation
It is a period of stabilization brought by growth and development.
CEPHALOCAUDAL GRADIENT OF GROWTH
This simply means that there is an axis of increased growth extending from the head towards feet. At about 3rd month of intrauterine life the head takes up about 50% of total body length. At this stage cranium is larger relative to face. In contrast the limbs are underdeveloped.
By the time of birth limbs and trunk have grown faster than head and the entire proportion of the body to the head has increased. These processes of growth continue till adult.
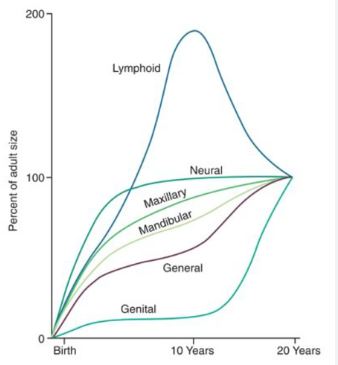
SCAMMON’S CURVE
In normal growth pattern all the tissue system of the body do not growth at the same rate. Scammon’s curve for growth shows 4 major tissue system of the body;
• Neural
• Lymphoid
• General: Bone, viscera, muscle.
• Genital
The graph indicates the growth of the neural tissue is complete by 6-7 year of age. General body tissue show an “S” shaped curve with showing of rate during childhood and acceleration at puberty. Lymphoid tissues proliferate to its maximum in late childhood and undergo involution. At the same time growth of the genital tissue accelerate rapidly.
Nail Biting Habits
Nail biting, also known as onychophagia, is one of the most common habits observed in children and can persist into adulthood. It is often associated with internal tension, anxiety, or stress. Understanding the etiology, clinical features, and management strategies for nail biting is essential for addressing this habit effectively.
Etiology
-
Emotional Problems:
- Persistent nail biting may indicate underlying emotional issues, such as anxiety, stress, or tension. It can serve as a coping mechanism for dealing with these feelings.
-
Psychosomatic Factors:
- Nail biting can be a psychosomatic response to stress or emotional discomfort, manifesting physically as a way to relieve tension.
-
Successor of Thumb Sucking:
- For some children, nail biting may develop as a successor to thumb sucking, particularly as they transition from one habit to another.
Clinical Features
-
Dental Effects:
- Crowding: Nail biting can contribute to dental crowding, particularly if the habit leads to changes in the position of the teeth.
- Rotation: Teeth may become rotated or misaligned due to the pressure exerted during nail biting.
- Alteration of Incisal Edges: The incisal edges of the anterior teeth may become worn down or altered due to repeated contact with the nails.
-
Soft Tissue Changes:
- Inflammation of Nail Bed: Chronic nail biting can lead to inflammation and infection of the nail bed, resulting in redness, swelling, and discomfort.
Management
-
Awareness:
- The first step in management is to make the patient aware of their nail biting habit. Understanding the habit's impact on their health and appearance can motivate change.
-
Addressing Emotional Factors:
- It is important to identify and treat any underlying emotional issues contributing to the habit. This may involve counseling or therapy to help the individual cope with stress and anxiety.
-
Encouraging Outdoor Activities:
- Engaging in outdoor activities and physical exercise can help reduce tension and provide a positive outlet for stress, potentially decreasing the urge to bite nails.
-
Behavioral Modifications:
- Nail Polish: Applying a bitter-tasting nail polish can deter nail biting by making the nails unpalatable.
- Light Cotton Mittens: Wearing mittens or gloves can serve as a physical reminder to avoid nail biting and can help break the habit.
-
Positive Reinforcement:
- Encouraging and rewarding the individual for not biting their nails can help reinforce positive behavior and motivate them to stop.
| Wire Size | Slot Size | Play (Degrees) |
|---|---|---|
| 21.5 x 28 | 0.022 " | 2° |
| 21 x 25 | 0.022 " | 4° |
| 19 x 25 | 0.022 " | 10° |
| Concept | Detail |
|---|---|
| Cephalogram film distance | 15 cm |
| Most posterior point of foramen magnum | Opisthion |
| Smile for diagnosis | Posed smile |
| Duchenne smile | Unposed smile |
| Ricketts esthetic line | Pronasale to chin |
| Yaw | Left-right movement of maxilla |
| Point O | Sassouni analysis convergence point |
| ANB angle | Riedel |
| Steiner's chevrons | ANB with incisor positions |
| COGS cephalometrics | Burstone & Legan |
| Beta angle | Baik & Ververidou |
| Jarabak ratio 58% | Vertical growth pattern |
| Nasal length:width ratio | 70% |
| Morley's ratio | 75 – 100% (incisor visibility) |
| Golden proportion | Ricketts; value = 62% |
| Connector value (central-lateral) | 40% |
| Buccal corridor value | ~13% |
| Eva point | Medial stress line confluence (Ricketts) |
Anchorage in orthodontics refers to the resistance that the anchorage area offers to unwanted tooth movements during orthodontic treatment. Proper understanding and application of anchorage principles are crucial for achieving desired tooth movements while minimizing undesirable effects on adjacent teeth.
Classification of Anchorage
1. According to Manner of Force Application
-
Simple Anchorage:
- Achieved by engaging a greater number of teeth than those being moved within the same dental arch.
- The combined root surface area of the anchorage unit must be at least double that of the teeth to be moved.
-
Stationary Anchorage:
- Defined as dental anchorage where the application of force tends to displace the anchorage unit bodily in the direction of the force.
- Provides greater resistance compared to anchorage that only resists tipping forces.
-
Reciprocal Anchorage:
- Refers to the resistance offered by two malposed units when equal and opposite forces are applied, moving each unit towards a more normal occlusion.
- Examples:
- Closure of a midline diastema by moving the two central incisors towards each other.
- Use of crossbite elastics and dental arch expansions.
2. According to Jaws Involved
- Intra-maxillary Anchorage:
- All units offering resistance are situated within the same jaw.
- Intermaxillary Anchorage:
- Resistance units in one jaw are used to effect tooth movement in the opposing jaw.
- Also known as Baker's anchorage.
- Examples:
- Class II elastic traction.
- Class III elastic traction.
3. According to Site
-
Intraoral Anchorage:
- Both the teeth to be moved and the anchorage areas are located within the oral cavity.
- Anatomic units include teeth, palate, and lingual alveolar bone of the mandible.
-
Extraoral Anchorage:
- Resistance units are situated outside the oral cavity.
- Anatomic units include the occiput, back of the neck, cranium, and face.
- Examples:
- Headgear.
- Facemask.
-
Muscular Anchorage:
- Utilizes forces generated by muscles to aid in tooth movement.
- Example: Lip bumper to distalize molars.
4. According to Number of Anchorage Units
-
Single or Primary Anchorage:
- A single tooth with greater alveolar support is used to move another tooth with lesser support.
-
Compound Anchorage:
- Involves more than one tooth providing resistance to move teeth with lesser support.
-
Multiple or Reinforced Anchorage:
- Utilizes more than one type of resistance unit.
- Examples:
- Extraoral forces to augment anchorage.
- Upper anterior inclined plane.
- Transpalatal arch.